


62° Congresso Nazionale ADOI, Firenze, 17-19 settembre 2026
Vol. 18 No. s1 (2026): 62° Congresso Nazionale ADOI, Firenze, 17-19 settembre 2026

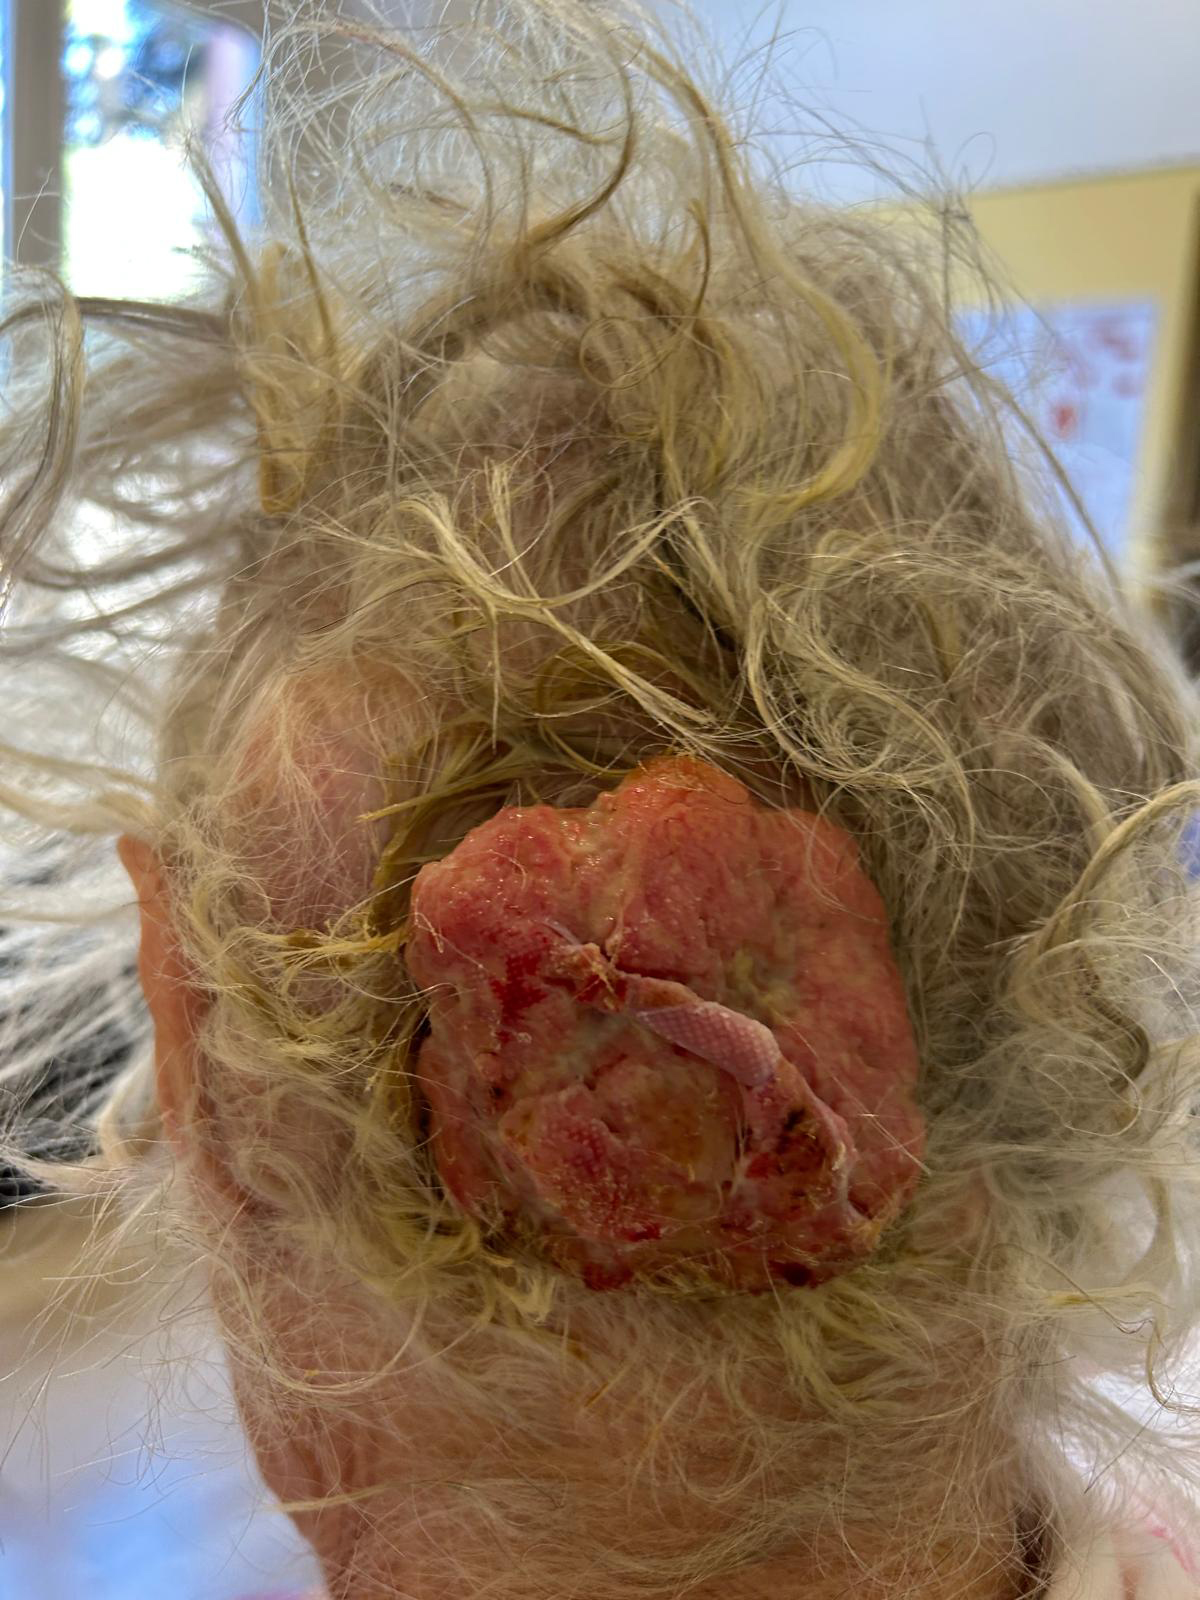
39 | WHEN BLISTERING DISEASE AND CUTANEOUS MALIGNANCY MEET: PARANEOPLASTIC BULLOUS PEMPHIGOID ASSOCIATED WITH SQUAMOUS CELL CARCINOMA
L. Melloni, M. A. Carpanese, D. Abbenante, M. Tabanelli | AUSL della Romagna, Ravenna, Italy
Publisher's note
All claims expressed in this article are solely those of the authors and do not necessarily represent those of their affiliated organizations, or those of the publisher, the editors and the reviewers. Any product that may be evaluated in this article or claim that may be made by its manufacturer is not guaranteed or endorsed by the publisher.
All claims expressed in this article are solely those of the authors and do not necessarily represent those of their affiliated organizations, or those of the publisher, the editors and the reviewers. Any product that may be evaluated in this article or claim that may be made by its manufacturer is not guaranteed or endorsed by the publisher.
Published: 24 September 2026
0
Views
0
Downloads
Authors
Downloads
Download data is not yet available.
Citations



1. Borradori L, Van Beek N, Feliciani C, Tedbirt B, Antiga E, et al. Updated S2 K guidelines for the management of bullous pemphigoid initiated by the European Academy of Dermatology and Venereology (EADV). J Eur Acad Dermatol Venereol. 2022 Oct;36(10):1689-1704. doi: 10.1111/jdv.18220. Epub 2022 Jun 29. PMID: 35766904.
2. Bishnoi A, Narang T, Handa S, Vishwajeet V, Saikia UN, et al. Paraneoplastic bullous pemphigoid associated with penile squamous cell carcinoma. J Eur Acad Dermatol Venereol. 2018 Apr;32(4):e140-e141. doi: 10.1111/jdv.14635. Epub 2017 Nov 2. PMID: 29024082.
3. Benhiba H, Hassam B. Association of bullous pemphigoïd and squamous cell carcinoma of the lip: a simple coïncidence? Pan Afr Med J. 2015 Apr 22;20:396. doi: 10.11604/pamj.2015.20.396.6804. PMID: 26185586; PMCID: PMC4499320.
4. Deguchi M, Tsunoda T, Tagami H. Resolution of bullous pemphigoid and improvement of vitiligo after successful treatment of squamous cell carcinoma of the skin. Clin Exp Dermatol. 1999 Jan;24(1):14-5. doi: 10.1046/j.1365-2230.1999.00396.x. PMID: 10233641.
5. Yamada T, Endo R, Tsukagoshi K, Fujita S, Honda K, et al. Aberrant expression of a hemidesmosomal protein, bullous pemphigoid antigen 2, in human squamous cell carcinoma. Lab Invest. 1996 Oct;75(4):589-600. PMID: 8874389.
6. Matsuoka Y, Yamada T, Seishima M, Hirako Y, Owaribe K, Kitajima Y. Transient translocation of hemidesmosomal bullous pemphigoid antigen 1 from cytosol to membrane fractions by 12-O-tetradecanoylphorbol-13-acetate treatment and Ca2+-switch in a human carcinoma cell line. J Dermatol Sci. 2001 Nov;27(3):206-14. doi: 10.1016/s0923-1811(01)00137-2. PMID: 11641060.
How to Cite
1.
39 | WHEN BLISTERING DISEASE AND CUTANEOUS MALIGNANCY MEET: PARANEOPLASTIC BULLOUS PEMPHIGOID ASSOCIATED WITH SQUAMOUS CELL CARCINOMA: L. Melloni, M. A. Carpanese, D. Abbenante, M. Tabanelli | AUSL della Romagna, Ravenna, Italy. Dermatol Reports [Internet]. 2026 Sep. 24 [cited 2026 Sep. 24];18(s1). Available from: https://journals.pagepress.net/dr/article/view/11099
Copyright (c) 2026 The Author(s)


This work is licensed under a Creative Commons Attribution-NonCommercial 4.0 International License.
